Live changeover status
A clock starts when the patient leaves theatre, and the screen shows where each team is. If the camera misses a step, staff can mark it by hand.
ORbserve is a camera system for operating theatres. When a case is closing, it tells recovery, cleaning and the porter at the same time, and records how long each part of the changeover takes.
It picks up the final count and dressing, and gives the next teams a few minutes' notice.
One tap on their phone, and recovery, cleaning and the porter are all called at once.
Patient out, cleaning, set-up and next patient in. Nobody has to write the times down.
The theatre in the film is a simulation, with stock footage from Pexels and an AI voice.
Live status during the changeover, a report afterwards, and one screen for the theatre coordinator.
A clock starts when the patient leaves theatre, and the screen shows where each team is. If the camera misses a step, staff can mark it by hand.
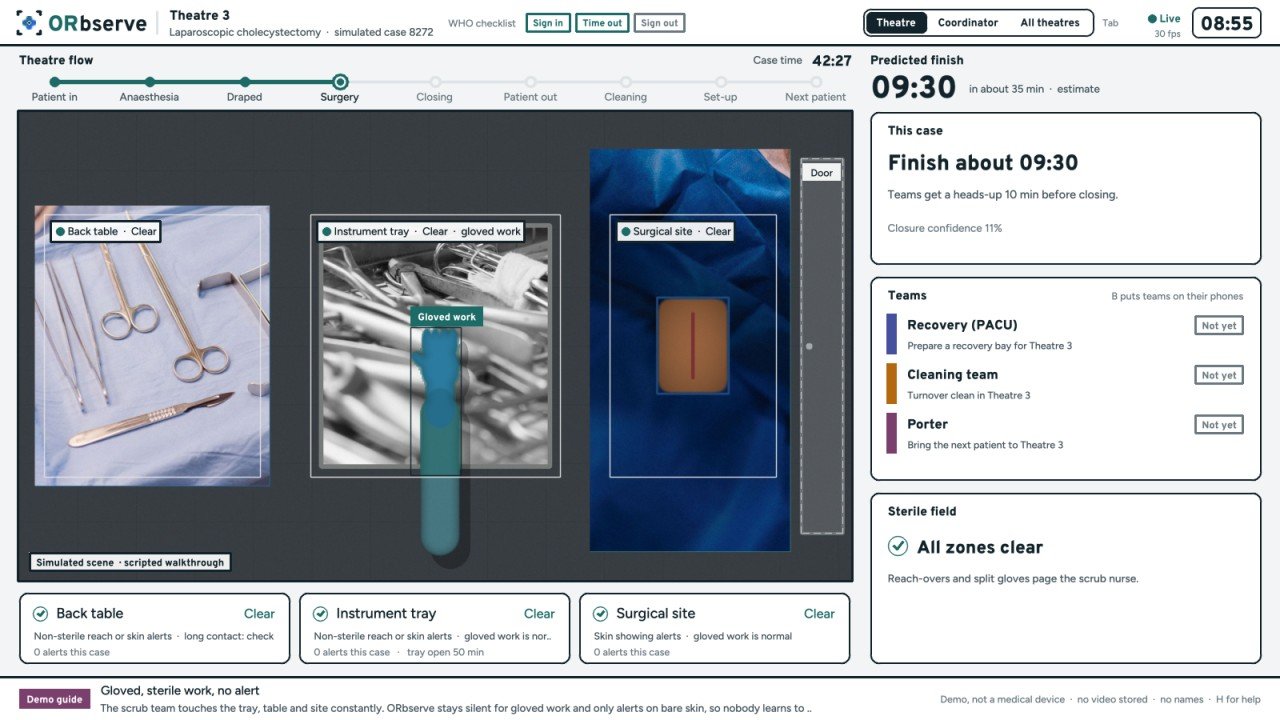
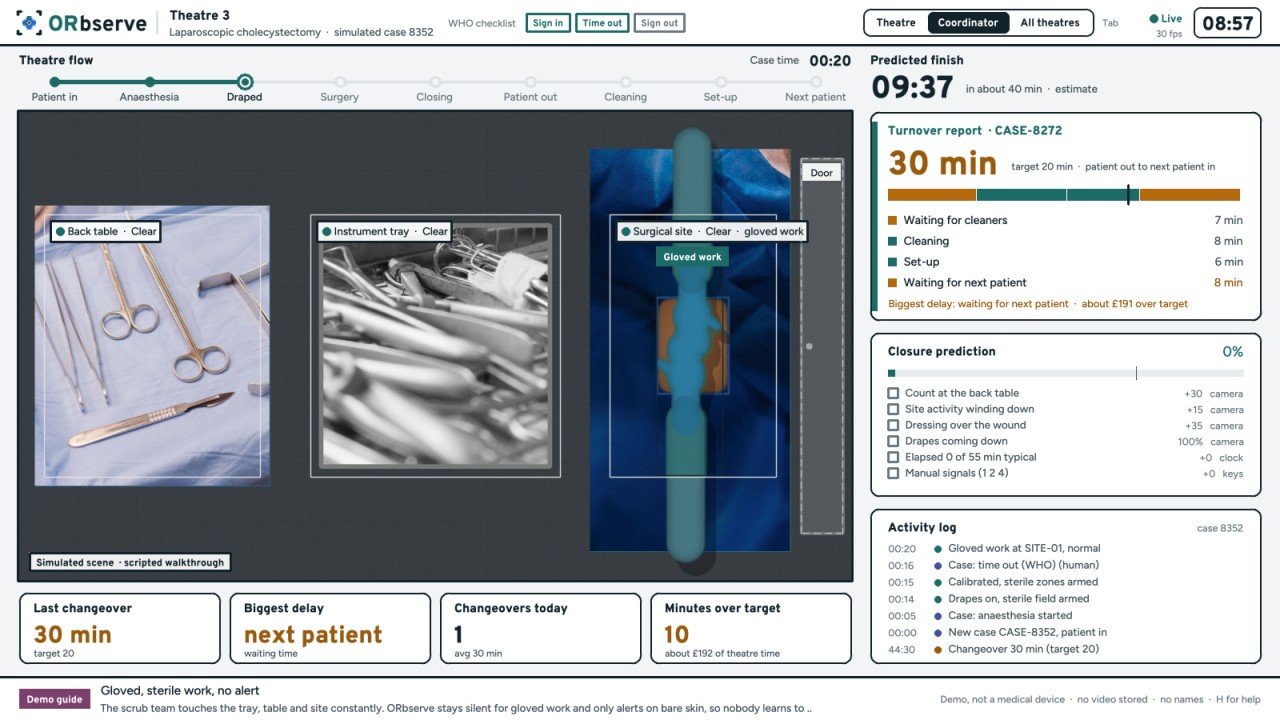
Each changeover is split into time spent waiting and time spent working. The report also records the standard theatre times, including anaesthetic start and knife to skin.
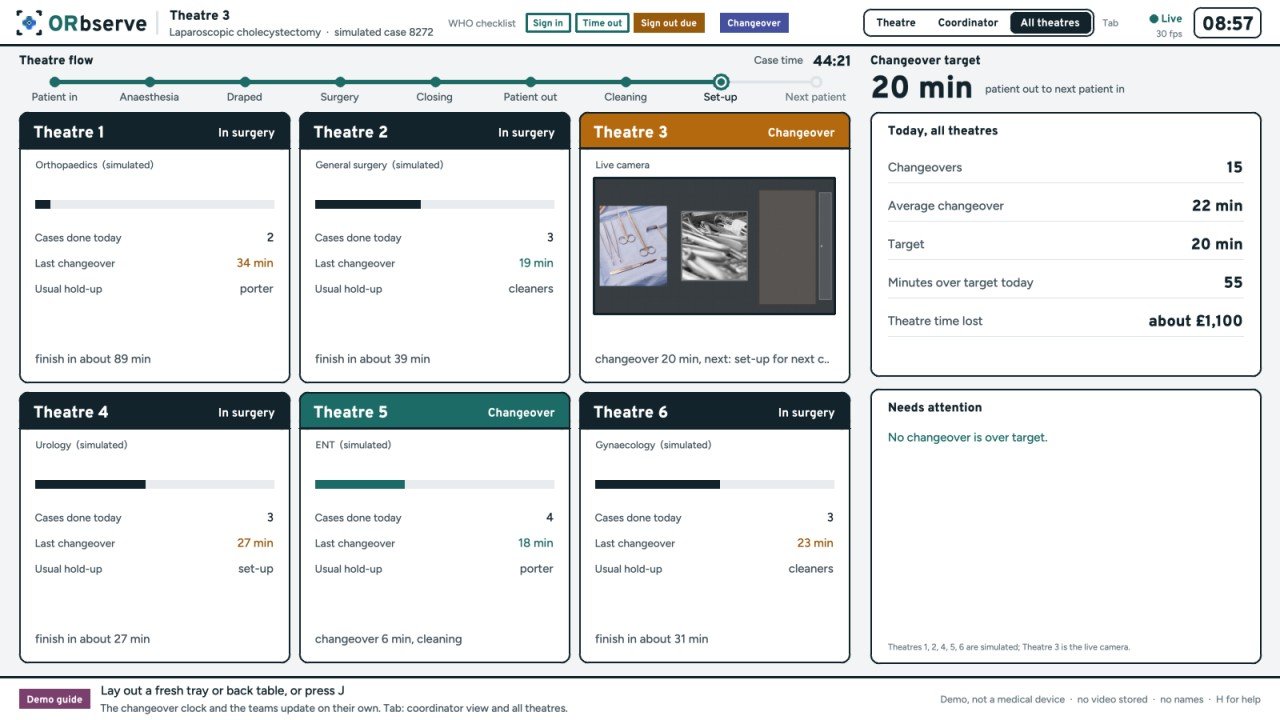
The coordinator can see which theatres are operating, which are being turned over, and which changeovers are running late.
ORbserve learns how long cases and changeovers actually take in your theatres, and uses that to help the coordinator plan the day. In development, built on the timings collected during a pilot.
Umbilical hernia repair from Thursday's waiting list. Predicted 38 min, patient is pre-assessed and available.
The changeover is predicted to finish at 13:03, so the patient arrives as the room is ready.
Predictions come from your own theatres, by procedure and surgeon, rather than the time booked on the list.
By mid-morning you can see whether a list is going to run late, early enough to move a case.
When a case is cancelled or finishes early, it suggests a suitable patient who can fill the time.
It tells the porter when to set off, based on when the room is predicted to be clean.
Each patient's latest time for clear fluids, updated if the list moves, so nobody fasts for hours longer than needed. The anaesthetist confirms.
A case that needs an ITU, HDU or ward bed, or special kit, is flagged until someone confirms it, so it isn't cancelled on the day.
A few written paragraphs for the coordinator on which lists look likely to overrun, and why.
Tomorrow's lists to every team at 7am, overrun warnings mid-morning, and free-slot alerts to the scheduling office.
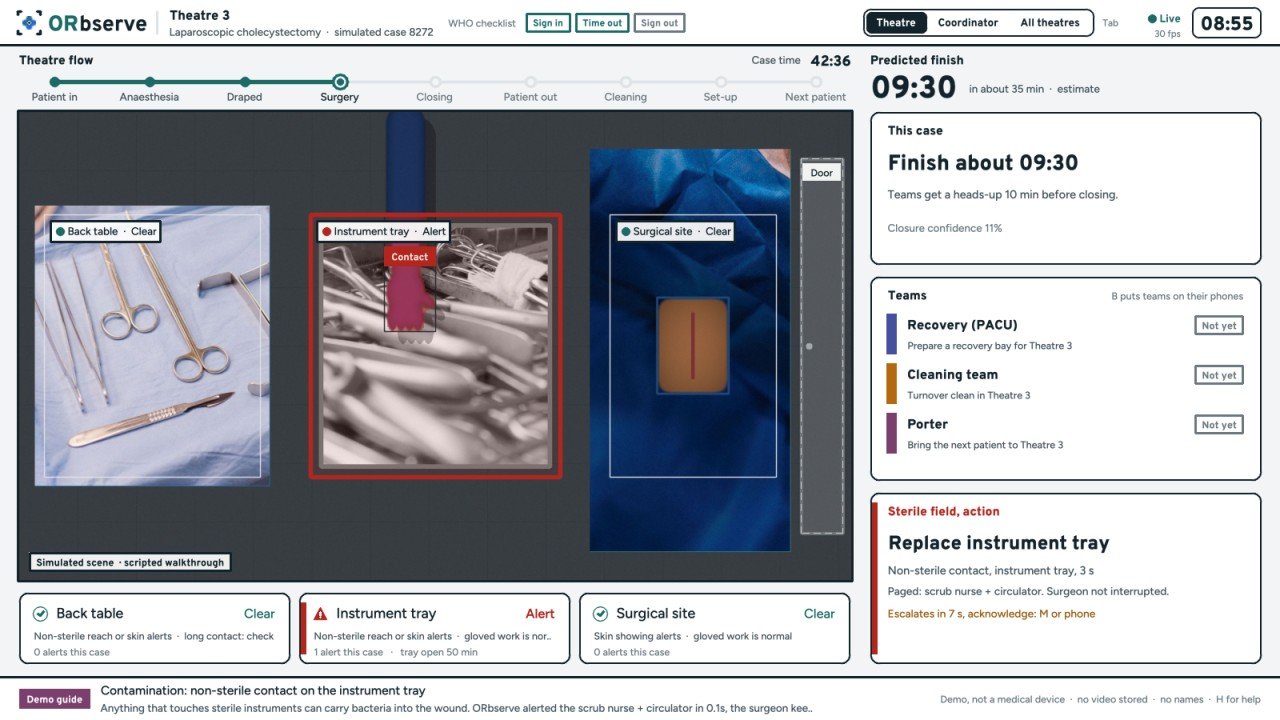
During surgery, the same camera watches the instrument tray, back table and surgical site. If something non-sterile touches them, the scrub nurse is paged and the surgeon isn't interrupted. During a pilot these alerts are only logged, not sent.
Record operations so they can be reviewed later. Useful for audits, but no help on the day.
Rely on times typed in by staff, which are often late or missing.
Works during the list: calls the next teams, records the times automatically and monitors the sterile field. No video is stored.
An example list in one theatre: five operations, four changeovers. Each gap looks small. Across a day they add up.
more operations a year could fit in England's theatres with better use of time
NHS Improvement, 2019what a minute of idle theatre time can cost, about £840–1,500 an hour
Wales Audit Office; St Mary's, LondonGIRFT's target for touchtime: anaesthetic start to the patient leaving theatre, as a share of list time
Getting It Right First TimePut in your own figures. Every box can be changed.
Each team is only told about its own part of the changeover.
A turnover report for every case, with the standard timestamps already filled in.
One board for every theatre: which changeovers are late, and what they're waiting for.
Called as soon as closure is confirmed, without watching the door or waiting for a phone call.
Called for the next patient at the right moment, with the ward and bay.
Told about five minutes before the patient leaves theatre, so a bay is ready.
An optional sterile-field watch that pages the scrub nurse, never the operating surgeon.
A pilot needs sign-off from several people. Here is what each of them usually asks.
You get the length of every changeover and what it was waiting on. After a few weeks you can tell whether a change you made helped.
No video, no faces, no staff scores, and staff can pause it. It goes in only after the theatre team has agreed, and a person always confirms closure.
Frames are analysed on a computer inside the theatre and discarded. Only event times are kept, and a data protection impact assessment is written with you before anything is installed.
For a pilot, nothing on the hospital network or the patient record system. One camera, one laptop, and a small Wi-Fi box for the team's phones that we bring.
Use the calculator above with your own numbers. The pilot gives you a measured figure for one theatre before any wider commitment.
Swipe for more
In 2024, nurses at a Boston hospital objected to cameras put in their theatres without warning. ORbserve is only installed once the theatre team has agreed.
One theatre for 60 days, compared with its own figures from before.
Meet the theatre team, agree what is measured, and write the data protection assessment with your IG lead.
The camera times every changeover without calling anyone, to give the theatre's own baseline.
Recovery, cleaning and the porter get their calls. The coordinator sees the board.
A short report: changeover times before and after, where the waiting went, and what staff thought.
Swipe for more
I'm Alannam Akabusi. I started ORbserve because a lot of theatre time is lost between operations, often because the next team finds out too late that they're needed. I think a camera and a phone alert can fix much of that without giving staff more to do.
Alannam Akabusi, founder
See ORbserve run a simulated theatre list, and talk through what a pilot in your theatre would involve.
From Alannam, the founder.
A simulated list on screen, and time for your questions.
60 days in one theatre, agreed with your team and IG lead.
Or email alannam@orbserve.co.uk
Documents you can share with your information governance lead or theatre team.
What it sees, what it keeps, what it never does, and how staff stay in control.
Data flow, storage, access and the NHS paperwork for a pilot, on one printable page.
The four waits inside a changeover, and which one to fix first.
What we agreed not to do with the camera, and why.
No. Each camera frame is analysed on a small computer in the theatre and then thrown away. What's kept is a list of events and times, such as "patient out, 14:02".
No. It tells people when it's their turn and shows where time was lost. Decisions stay with the team, and a person always confirms closure.
One theatre for 60 days. We agree it with the theatre team first, set up one camera and a laptop, measure the theatre's changeovers for two weeks as a baseline, then switch on the team calls and compare.
About an hour in theatre: the camera goes above the operating table, the zones are drawn on screen, and the team's phones are connected. Nothing is installed on hospital computers.
Today, a working prototype tested in a simulated theatre and on a mock table. Shorter changeovers from similar tools are reported in the US. ORbserve's own evidence will come from the first NHS pilot, measured against that theatre's baseline.
The changeover features are operational software. The sterile-field alerts would likely be regulated as medical-device software (MHRA), so in a pilot they run in observation mode, logging what they would have flagged, until that route is complete with a clinical partner.